When a Toothache Becomes a Dental Emergency

A toothache has a way of shrinking the world. Work becomes harder to focus on, meals turn into a negotiation, sleep gets interrupted, and even normal conversation can feel irritating. Most people have had some version of tooth pain at some point, and many assume it will settle down on its own. Sometimes it does. Quite often, though, pain is the first sign that something deeper is already underway.
The difficult part is that not every toothache means the same thing. One person may have brief sensitivity from a worn filling and be fine with a routine dental visit. Another may have a deep infection building pressure inside the tooth, with swelling that can move quickly from uncomfortable to dangerous. Knowing the difference matters, not only for comfort, but for safety.
A true dental emergency is not just about how much something hurts. Severity matters, but so do timing, swelling, trauma, bleeding, and the risk that an infection is spreading. If you have ever wondered whether you need to wait for a regular appointment or call an Emergency Dentist right away, the answer depends on a few very specific warning signs.
Why toothaches can turn serious so quickly
The structure of a tooth explains a lot about why pain can escalate. On the outside, enamel is hard and protective. Underneath sits dentin, which is less dense and more sensitive. At the center is the pulp, a small space containing nerves and blood vessels. Once decay, a crack, or deep wear reaches that inner tissue, the tooth can become inflamed or infected.
What surprises many patients is how little room there is inside a tooth. Inflammation in that confined space creates pressure. Pressure on the nerve creates pain, often intense and throbbing. If bacteria gain access to the pulp and the tissue begins to die, the infection can move out through the root tip and into the surrounding bone and gum. That is when swelling often appears.
At that stage, the problem is no longer just "a bad toothache." It can become an abscess, a spreading infection, or a situation where the tooth may no longer be saved if treatment is delayed too long. I have seen patients try to push through several days with painkillers, only to come in with a face noticeably swollen on one side and a fever that started the night before. The difference between a manageable procedure and an urgent intervention can be just a matter of time.
Pain that sounds ordinary but should not be ignored
Tooth pain rarely reads like a textbook. Some people feel a sharp zing with cold drinks. Others describe a dull ache in the jaw that they cannot pinpoint. Referred pain is common, especially in the back teeth. A lower molar can make the ear ache. A cracked upper tooth can feel like sinus pressure. That is why relying on location alone can be misleading.
A few patterns deserve closer attention. Pain that wakes you up at night is rarely trivial. So is pain that lingers after hot or cold exposure rather than fading within a second or two. Throbbing pain, pain that worsens when you lie down, and pain that becomes stronger over several days all suggest that the inner nerve tissue may be involved.
Then there is biting pain. If a tooth feels high, sore, or sharply painful when you chew, the cause may be a crack, an inflamed ligament, or an infection around the root. Patients often say, "It only hurts when I bite on it," as if that makes it less urgent. In fact, that pattern can point to a fracture or abscess that needs prompt evaluation.
The signs that move a toothache into emergency territory
Pain is only one piece of the picture. Dentists look for signs that the problem may threaten the tooth, the surrounding tissues, or the patient's general health. A toothache should be treated as an emergency when it comes with any of the following:
- visible swelling of the gum, face, or jaw
- fever, chills, or a general sick feeling alongside the tooth pain
- difficulty swallowing, opening the mouth, or breathing normally
- uncontrolled bleeding after trauma or dental treatment
- a broken, knocked-out, or significantly displaced tooth
Swelling is especially important. A localized pimple-like bump on the gum may signal a draining abscess. Diffuse swelling in the cheek or under the jaw can mean the infection is spreading through soft tissue spaces. If the swelling affects the floor of the mouth, speech, swallowing, or breathing, that is an urgent medical situation, not something to monitor until morning.
Fever changes the equation too. Dental infections do not always cause it, but when they do, the body is telling you the problem is no longer contained. Patients sometimes say they "just feel off" or unusually tired. That matters. An infection in the mouth can affect more than the tooth itself.
When severe pain is not the only danger
Some of the most serious dental emergencies are not the most painful. A knocked-out permanent tooth may hurt less than an abscessed molar, yet the timeline for saving it is far tighter. Similarly, a cracked tooth can be unstable without causing dramatic symptoms at first. Trauma after a fall, sports injury, or car accident may leave the mouth looking mostly normal while deeper damage is present.
Children add another layer of complexity. A child with a toothache may not describe the pain clearly. They may simply stop chewing on one side, wake at night crying, or refuse foods they normally like. Facial swelling in a child deserves prompt evaluation, because infections can progress quickly.
Adults with certain medical conditions also need a lower threshold for urgent care. Diabetes, immunosuppression, recent chemotherapy, certain heart conditions, and medications that affect healing can turn a dental problem into a more complicated event. Pregnancy is another case where timing and treatment choice matter, though pain and infection should still be assessed promptly rather than postponed.
The common causes behind emergency tooth pain
Deep tooth decay is one of the biggest drivers of emergency visits. Small cavities often cause no symptoms. Once decay gets close to the nerve, patients may notice sensitivity to sweets or cold. When the pulp becomes inflamed, the pain can become spontaneous and severe. If the nerve dies, there may be a brief period where the pain seems to lessen, only for pressure and swelling to appear later as infection spreads beyond the tooth.
Cracks are another frequent culprit. Some cracks are visible and obvious after biting something hard. Others are microscopic and difficult to detect. A patient may report a sharp pain on release when chewing, especially with nuts, crusty bread, or ice. These teeth can be tricky because they may look intact while producing significant symptoms.
Gum infections can mimic toothaches as well. A food trap between teeth, a deep periodontal pocket, or advanced gum disease can create localized pain and swelling. Wisdom teeth, especially when partially erupted, are notorious for this. The gum tissue around them can become inflamed and infected, leading to pain that radiates into the jaw and throat.
Then there are failed restorations. Old fillings leak. Crowns loosen. Root canal treated teeth can develop new infections years later. A previous history of dental work does not guarantee a tooth is out of danger. In practice, some of the most urgent calls come from patients who assumed a crown or root canal meant that tooth was permanently "fixed."
What an Emergency Dentist is trying to determine
When you call with a toothache, the goal is not just to book a slot. The office is usually trying to sort urgency. A good triage conversation helps determine whether you need same-day care, next-day care, or immediate referral to urgent medical services.
The dentist is usually listening for clues. When did the pain start? Is it constant or triggered? Is there swelling? Do hot and cold make it worse? Can you point to one tooth? Was there recent trauma? Are you having trouble swallowing or breathing? Are you running a fever? The answers help narrow the likely cause and identify red flags.
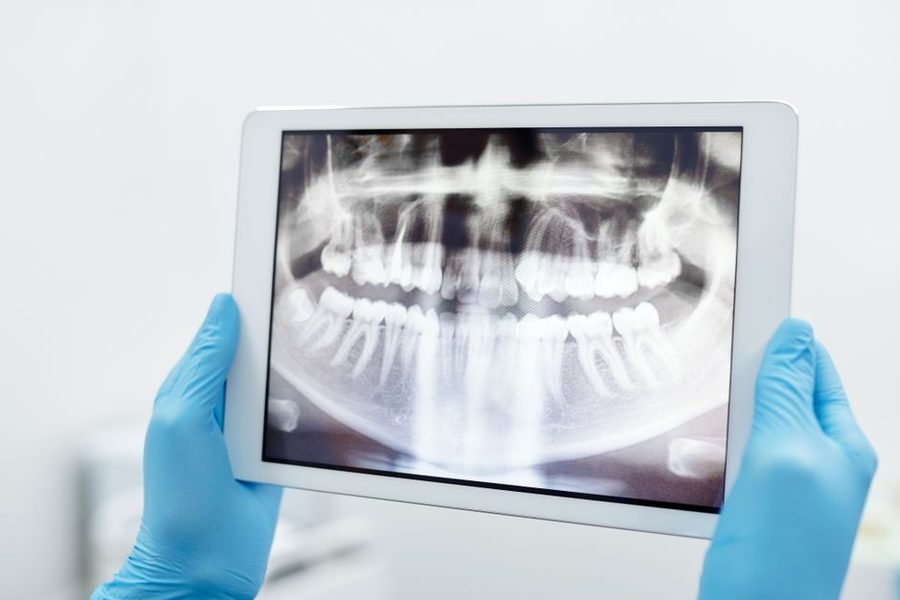
At the appointment, the exam often includes a visual inspection, percussion on the teeth, temperature testing, bite testing, and X-rays. These are not routine formalities. Each one helps distinguish between reversible irritation, deep nerve inflammation, abscess formation, fracture, gum-related pain, or referred pain from another area.
Sometimes patients expect the final treatment to happen immediately and permanently in a single visit. Often that is possible. Sometimes it is not. In an emergency setting, the first priority may be to stop the pain, control infection, and stabilize the situation. Definitive treatment, such as a root canal, crown, extraction, or specialist procedure, may happen the same day or may need to follow shortly after.
What you can do at home while waiting to be seen
A short delay of a few hours is common, and what you do during that window matters. Start with simple, low-risk steps that reduce irritation and avoid making the problem worse.
- rinse gently with warm salt water
- use a cold compress on the outside of the face if swelling is present
- take over-the-counter pain medication as directed, if you can safely use it
- keep the area as clean as possible without aggressive poking or flossing
- avoid placing aspirin, alcohol, or home remedies directly on the tooth or gum
That last point is worth stressing. People still try to "burn out" tooth pain with clove oil, liquor, crushed tablets, or aspirin held against the gum. These measures can irritate or chemically burn soft tissue and do nothing to treat the source of the problem.
If a permanent tooth has been knocked out, handle it by the crown rather than the root, rinse it gently if dirty, and try to place it back in the socket if you can do so safely. If not, store it in milk or in the person's saliva and seek care immediately. Time matters greatly in those cases.
If a tooth breaks, save any fragments if possible. If a filling or crown comes off, keep it and bring it with you. None of these objects can always be reused, but sometimes they help guide repair.
When antibiotics help, and when they do not
There is persistent confusion around antibiotics and toothaches. Many patients expect them, especially if pain is severe. Yet a large number of dental pain episodes are caused by inflammation inside the tooth, not an active spreading infection in surrounding tissues. In those cases, antibiotics often provide little to no benefit. The source needs dental treatment, not just medication.
Antibiotics are more likely to be indicated when there is swelling, spreading infection, fever, or a clear sign that bacteria have moved beyond the tooth into nearby tissues. Even then, they are usually an adjunct, not the main treatment. An abscess often needs drainage, root canal treatment, extraction, or another direct procedure. Medication alone may buy time, but it rarely solves the problem fully.
This is one of the reasons delayed care can backfire. A patient may get a temporary reduction in symptoms after antibiotics from urgent care or an emergency department, then assume the issue is gone. Weeks later, the same tooth flares again, often worse than before. The underlying cause was never removed.
Cases that surprise people
Some patterns catch patients off guard because they do not match the usual image of a "dental emergency."
One is the cracked tooth that only hurts with certain foods. A patient may tolerate soft meals all week, then feel a sharp stab when chewing granola or a seed. Because the pain is intermittent, they postpone care. Yet those small repeated episodes can signal a fracture line that deepens over time.
Another is the old root canal tooth that becomes tender to pressure. Since the nerve was already removed, patients assume it cannot become infected again. It can. Bacteria can re-enter through a leaking crown, a missed canal, recurrent decay, or a crack in the root.
A third is sinus-related confusion. Upper molar pain and sinus pressure can overlap so closely that patients are convinced they have one when it is really the other. A good exam, and often a dental X-ray, helps separate them. Sometimes both are present at once, which makes self-diagnosis even less reliable.
The cost of waiting
People put off emergency dental visits for understandable reasons. Cost is a real concern. So is time away from work, fear of treatment, and the hope that the pain will just stop. But delay often raises both the biological cost and the financial one.
A tooth that might have been treated with a filling can progress to needing root canal therapy and a crown. A tooth that might have been saved with a root canal can become so structurally compromised or infected that extraction is the only realistic option. Swelling can lead to missed work, poor sleep, dehydration, and emergency room visits that provide temporary support but not definitive dental care.
There is also a quality-of-life cost that is easy to underestimate. People with ongoing dental pain often eat less, chew on one side, sleep poorly, and become irritable without realizing how much the problem is affecting them. By the time they seek care, they are not just dealing with a toothache. They are dealing with several days of accumulated strain.
How emergency care is different from routine dental care
Routine dentistry is preventive and planned. Emergency care is focused, fast, and problem-centered. The appointment is built around identifying the source of acute symptoms, ruling out dangerous complications, and delivering immediate relief where possible.
That may mean opening a tooth to relieve pressure, adjusting a traumatic bite, draining an abscess, prescribing medication when appropriate, stabilizing a fracture, or extracting a tooth that cannot be saved. It may also mean deciding that the safest next step is referral to an endodontist, oral surgeon, or hospital-based service if the case is beyond what should be managed in a general office setting that day.
An experienced Emergency Dentist also pays attention to what patients may underreport. Some minimize swelling because they do not want to "make a fuss." Others overfocus on one painful tooth when the true source is nearby. Clinical judgment matters here. The right treatment is not always the most obvious one from the patient's perspective.
Preventing the next emergency
Most dental emergencies are not random. They are often the final stage of a process that started months or years earlier. Small cavities, old restorations, clenching and grinding, untreated gum disease, neglected wisdom teeth, and missed recall visits all raise the odds that pain will eventually demand urgent attention.
Prevention is not glamorous, but it is effective. Regular exams catch decay while it is still small. X-rays reveal hidden issues between teeth and under existing dental work. Night guards reduce the repeated stress that can crack teeth or inflame the bite. Prompt repair of a broken filling is usually far easier than dealing with the same tooth after the nerve is involved.
Even people with good habits can develop emergencies. Teeth fracture. Fillings fail. Accidents happen. But patients who stay engaged with routine care usually face less severe problems and more treatment options when something does go wrong.
The moment to act
A mild toothache after biting into ice may not require panic. A little cold sensitivity around a recently filled tooth may settle. Dentistry involves judgment, not alarmism. Still, certain symptoms should prompt action rather than patience.
If the pain https://www.google.com/maps?cid=17479708580987630325 is severe, if it lingers, if your face or gums are swelling, if you have fever, if chewing becomes difficult, or if trauma has damaged a tooth, it is time to call. The right question is not whether you can endure it until tomorrow. The right question is whether waiting risks losing the tooth, worsening the infection, or placing your health under unnecessary strain.
Toothaches are common. Dental emergencies are common too. The line between them is clearer than many people think once you know what to watch for. Pain with swelling, pain with systemic symptoms, pain after trauma, and pain that intensifies rather than fades all deserve prompt professional attention. When those signs appear, getting examined quickly is not overreacting. It is sound clinical judgment.
Smyle Dental Bakersfield
2016 E St, Bakersfield, CA 93301, United States
+16614939040
FAQ About Emergency Dentist
What counts as a dental emergency?
Severe tooth pain, facial swelling, uncontrolled bleeding, a knocked-out or displaced tooth, and significant dental trauma may need prompt assessment. Trouble breathing or rapidly increasing swelling requires urgent medical help.
What should I do if a permanent tooth is knocked out?
Handle the tooth by the crown rather than the root, keep it moist, and contact a dentist immediately. Fast treatment can improve the chance of saving the tooth.
Can an emergency dentist treat severe tooth pain the same day?
Same-day care may be available depending on the cause and schedule. The dentist will examine the area, may take digital X-rays, and recommend treatment based on the diagnosis.
Should I go to the emergency room for dental swelling?
Seek urgent medical care for trouble breathing, difficulty swallowing, rapidly spreading facial swelling, or other severe symptoms. A dentist can assess the underlying dental cause and provide appropriate follow-up care.